
Investing in Access: Financing Sickle Cell Care in Africa
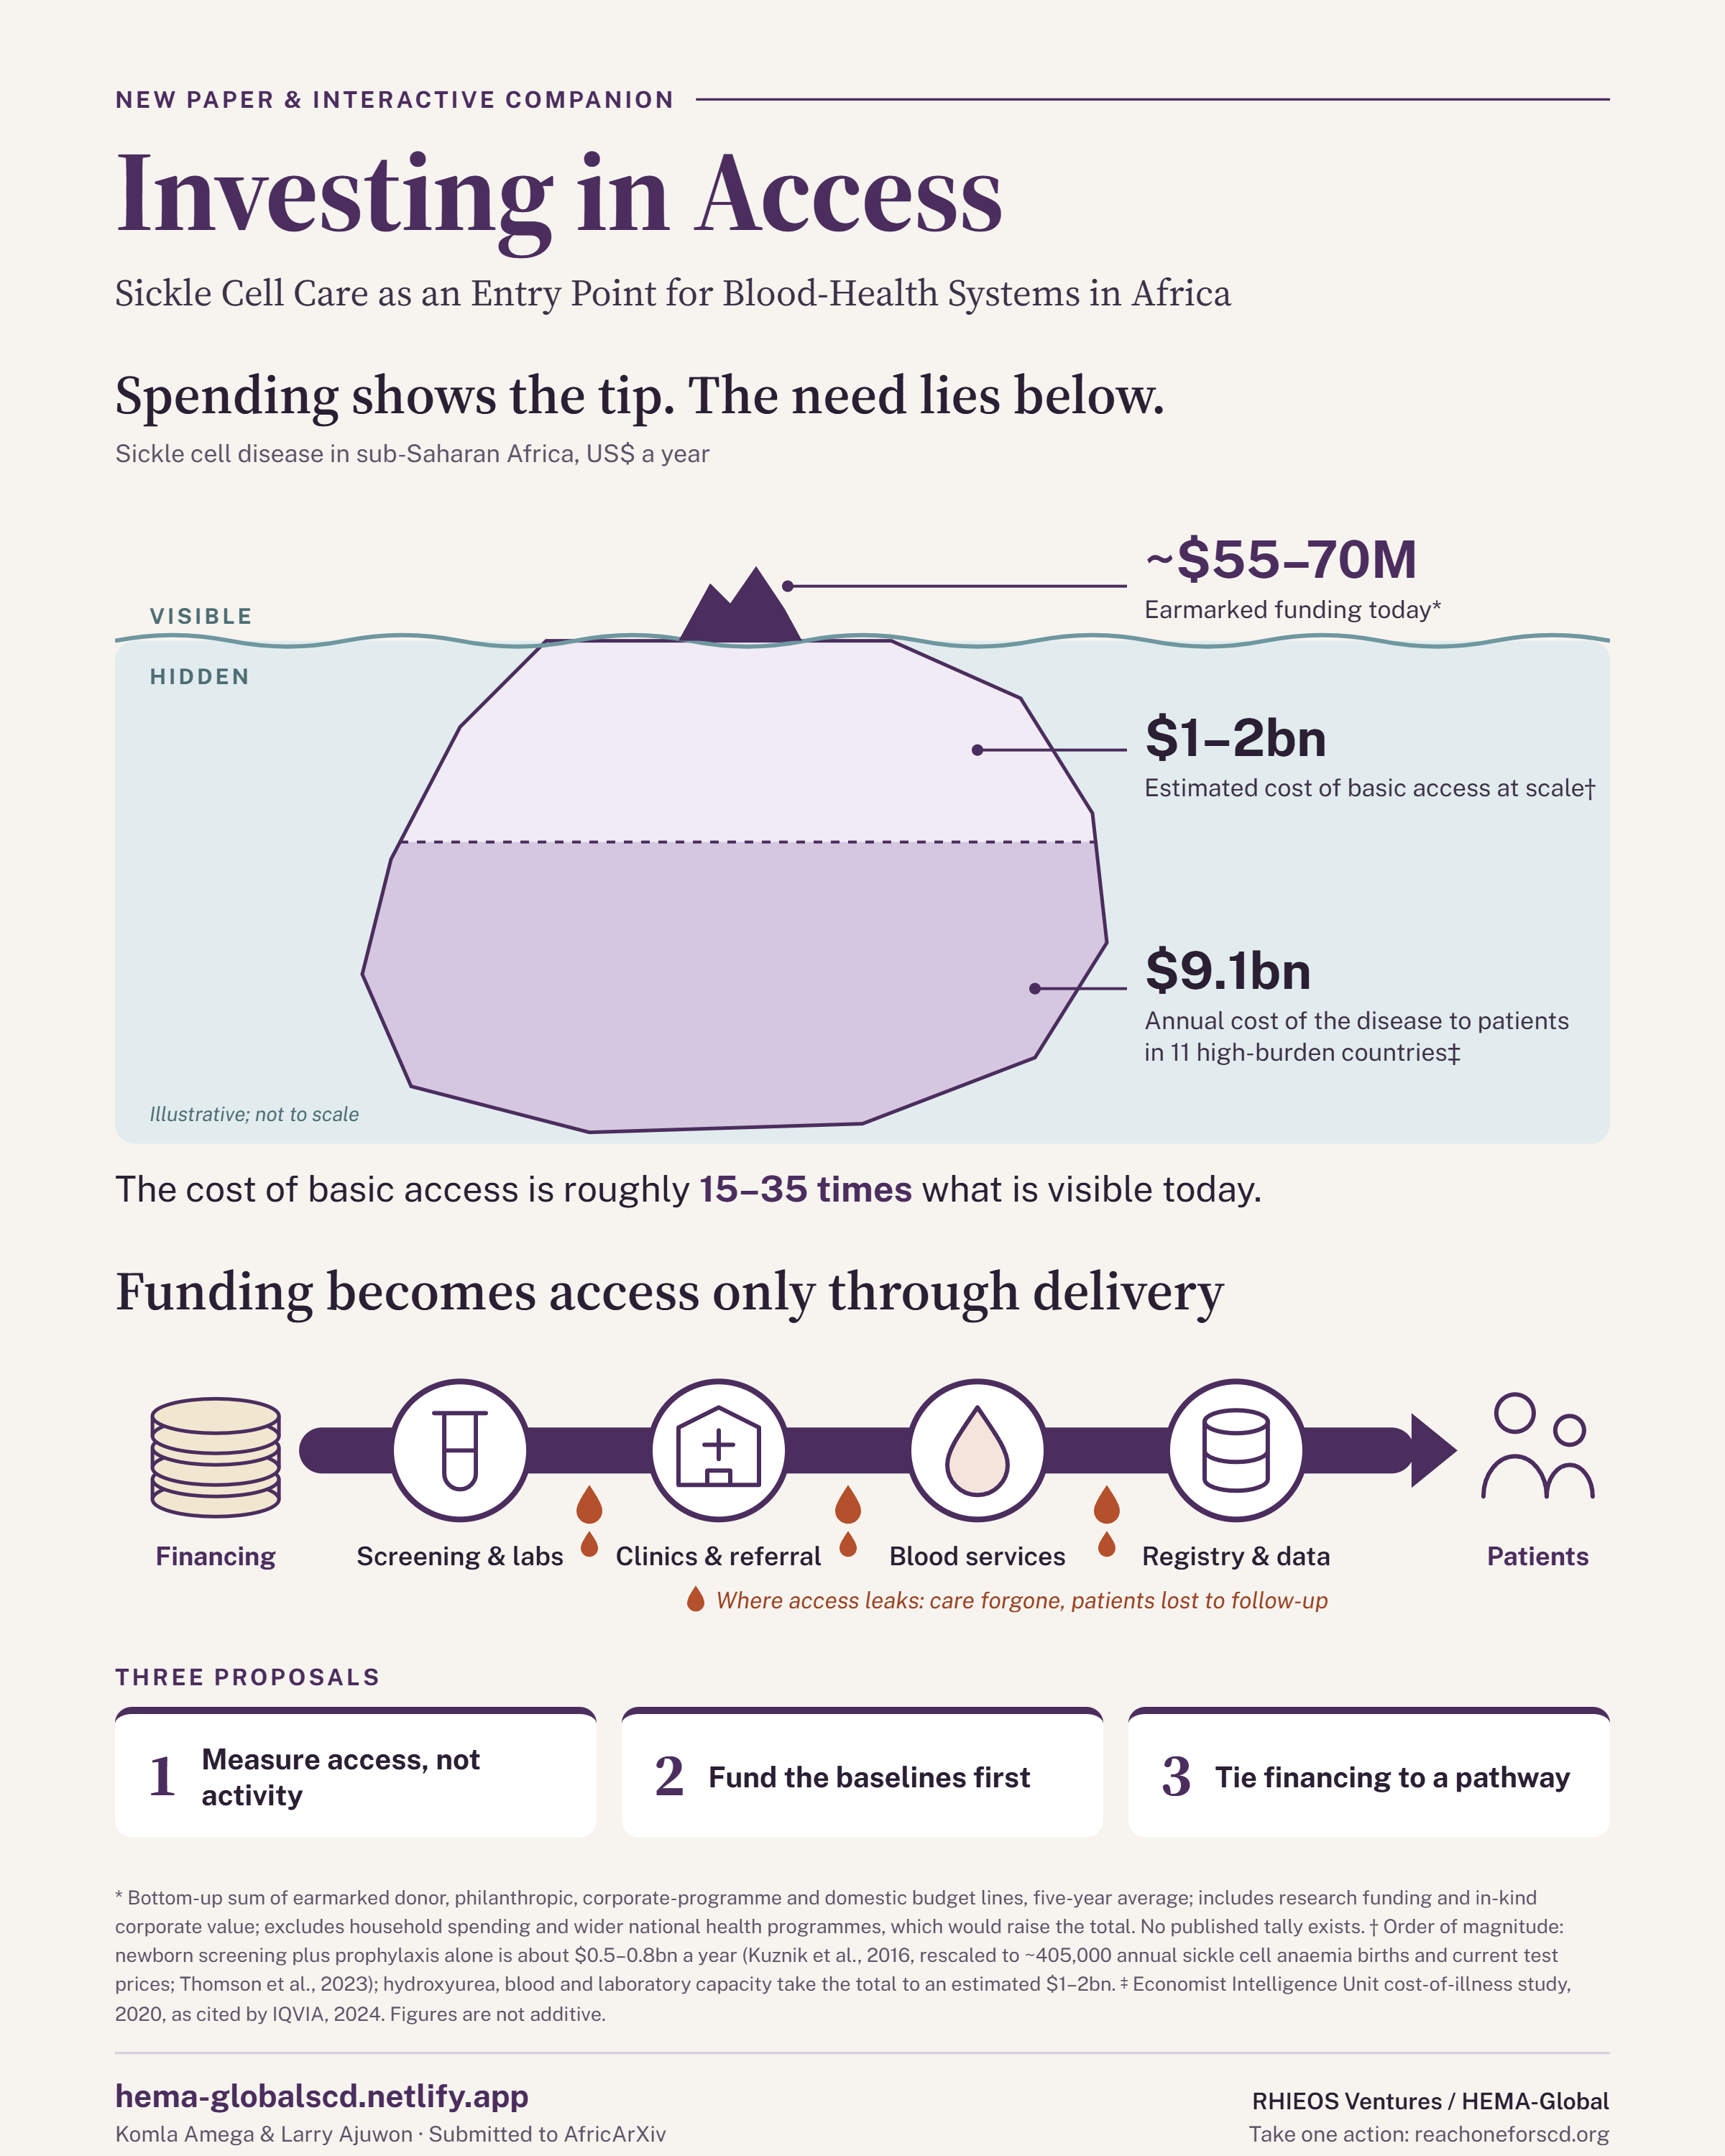
The central investment problem in sickle cell disease (SCD), and in blood health more broadly, is the lack of a coordinated way to finance access. Because SCD spans blood health, chronic care, and maternal and child health, that gap weakens far more than a single disease programme.
Where public investment and coverage are limited or absent, families bear most of the cost of care. Need that is paid for privately, deferred or forgone leaves little trace in expenditure data, so budgets capture only part of the demand and miss the need that most requires a response.
Financing access therefore needs to begin with a different evidence base. Investing in Access: Sickle Cell Care as an Entry Point for Blood-Health Systems in Africa, by Komla Amega and Larry Ajuwon, proposes access intelligence: the integration of registry, service, patient, cost and capacity data. Together, these locate where care breaks down, identify the capability that is missing, and match each gap to an appropriate form of financing.
Financing mechanisms determine where money comes from but do not decide where investments need to go. The paper rejects a single, fixed sequence for strengthening systems. In some settings, foundational capacity must come first; in others, a targeted intervention can generate momentum for broader reform. The question for policymakers and investors is what is missing, what would close the gap, and how it should be financed.
The paper makes three proposals, each of which any government, funder, patient organisation or diaspora partner can take up independently:
Adopt access measures with published baselines: diagnosis before the first birthday, completion of scheduled follow-up, and uninterrupted access to hydroxyurea.
Fund those baselines as a costed first-phase deliverable in at least one high-burden country, so later investment can be judged against them.
Match financing mechanisms to a pathway, so that diaspora and pooled funds are tied to a defined clinical pathway and a registry able to report against it.
This is why SCD is an entry point. Investment in access to SCD care builds the screening, laboratory, blood-service, referral, and data capacity on which wider blood-health systems depend.
Read the paper and explore the interactive companion: https://hema-globalscd.netlify.app
Submitted to AfricArXiv; preprint forthcoming.
Take one action: https://reachoneforscd.org
RHIEOS Decision Intelligence — Public Beta
Today we're opening a new public version of RHIEOS. It's the most significant change in how we've organised and presented our work since TrialValue® was launched in 2015.
In February, I wrote about why clinical trials need Decision Intelligence: execution systems have become far more sophisticated, but the choices that shape outcomes — around economics, collaboration and governance — still depend on fragmented information and individual judgement.
Since then, we've been building toward this. Work on incentive design and CRO selection led to early Decision Intelligence prototypes, shared privately with clients and colleagues. More recently, that work extended into AI assurance for GxP. This release brings those strands together for the first time.
Asset Value — reframing clinical development's scientific and investment value
Assurance — strengthening judgement and control in AI-supported GxP processes
Access — improving patient and market access, and reducing trial burden
Organisational Learning — helping teams learn from choices, outcomes and experience
Different areas, one question: how do life-science organisations learn better, decide well and create value?
The site also opens part of our knowledge base through Open Resources — papers, models and reference material that can be read, downloaded, used and challenged. Selected resources are released under CC BY 4.0, while detailed methods and software remain protected.
The aim is not simply to describe our work. It is to make part of it useful in its own right — and open enough to be questioned, tested and improved.
Public Beta is open now.
Explore it. Use the resources. Question the assumptions. Tell us how to improve it.
https://rhieosbeta.netlify.app
RHIEOS Fireside Autumn 2026 Cafe Session
How do biotech organisations build the capacity to decide well, learn systematically and create value.
This October, RHIEOS will convene a small group of senior leaders in Amsterdam for: Decision Systems & Practices for Knowledge and Value Creation in Biotech.
A focused roundtable on decision intelligence, organisational learning and AI assurance and their role in strengthening judgement and extending capabilities.
Date: w/c 19 October 2026 | AmsterdamBy invitation | Chatham House Rule | Participation fee applies
Request an invitation: info@rhieosventures.co.uk
RHIEOS Fireside Decision Room 01: Designing Incentives in CRO Selection

A private 40-minute RHIEOS discussion for leaders involved in clinical outsourcing, procurement, alliances, partnering, and study execution.
We are planning a small working conversation on what changes when decision logic, incentive criteria, and weighting assumptions are made explicit from the outset.
Private hybrid session | Live only | Not recorded
Planned for mid-May 2026 | Final date to be confirmed
Request an invitation: info@rhieosventures.co.uk
“our “simple task” as a research-to-care enterprise is to ensure that we keep to our ethical foundational principles constant”